Turn clinical evidence into defensible action.
Connect claims, encounters, clinical documents and member data. InferonIQ identifies supporting evidence, validates HCCs, surfaces suspected missing conditions, turns documentation gaps into a retrieval worklist and creates a traceable review workflow for Medicare Advantage Risk Adjustment, RADV and coding teams.
Evidence-linked · Human-reviewed · Second-level QA · Audit-ready · BYOC
HCC 37 · Diabetes with chronic complications
Reported on claim, but no current-year encounter documents MEAT for the complication.
Claim 837P · DOS 2026-03-14
ICD-10 E11.22 reported
Progress note · 2025-11-02
p.3 — “DM2 with CKD stage 3”
Lab panel · 2026-02-20
eGFR 52 mL/min
From chart to finding, in one view.
Reported HCCs reconciled against encounters and clinical documents, with the evidence one click away.
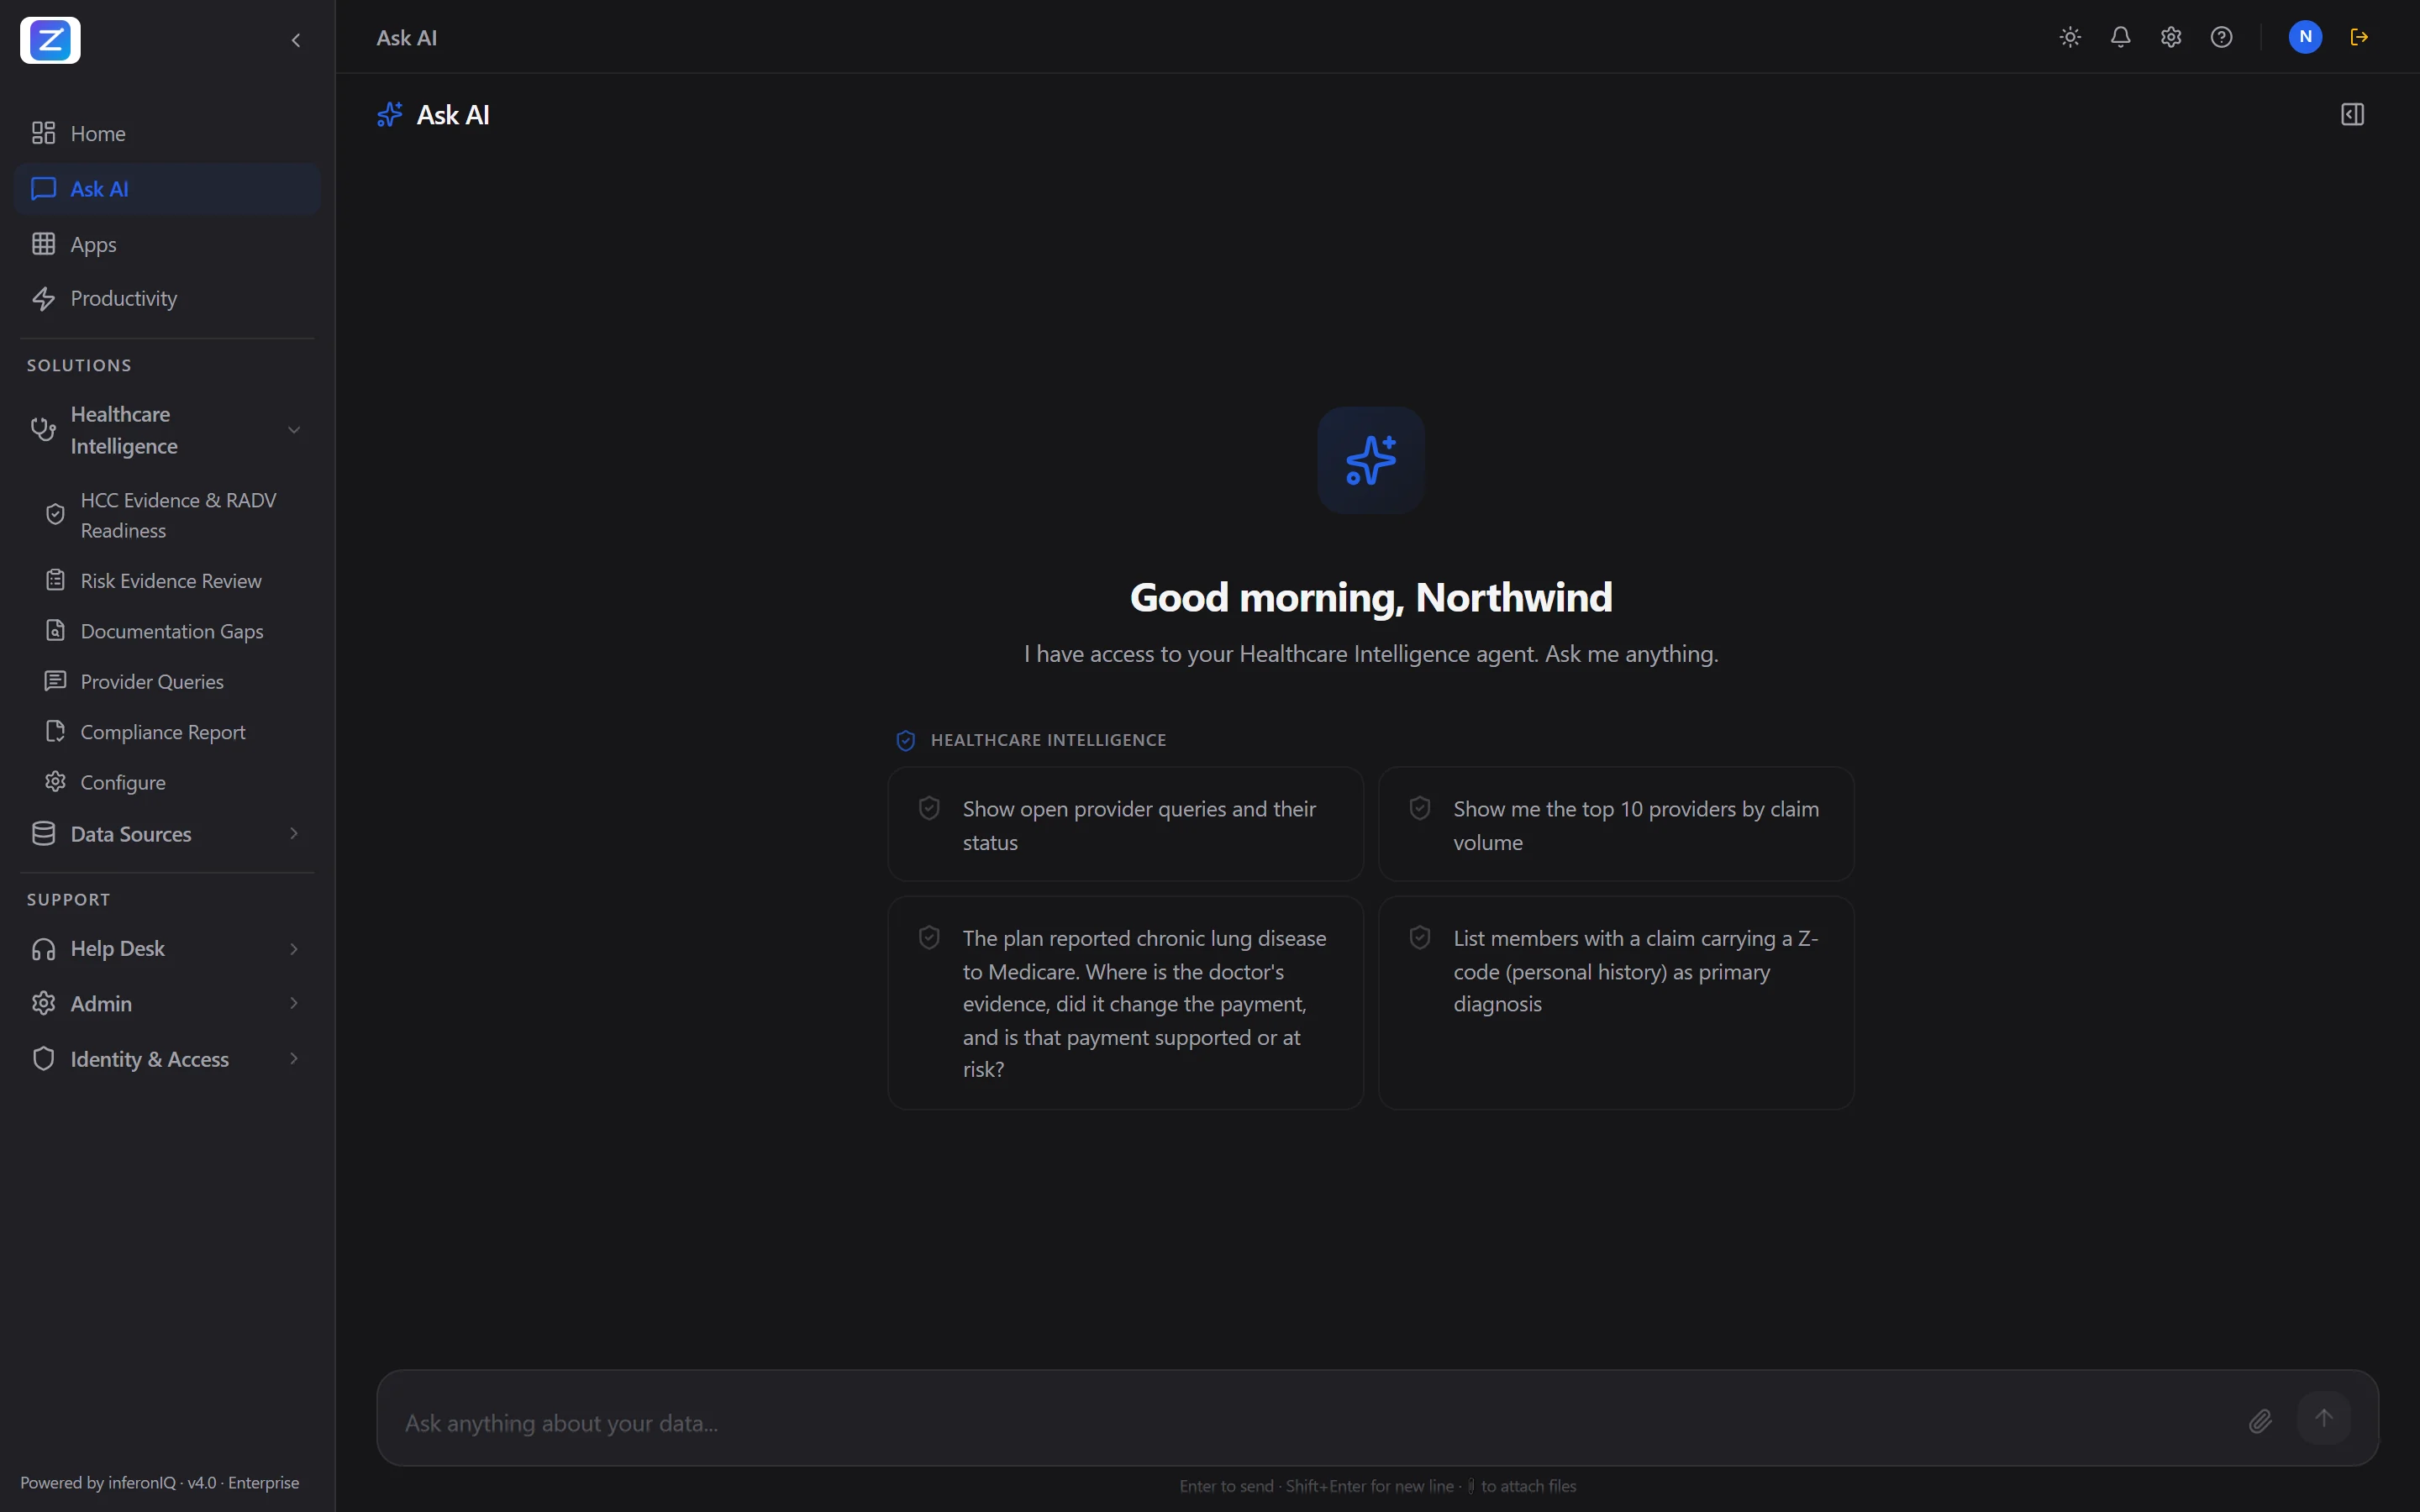
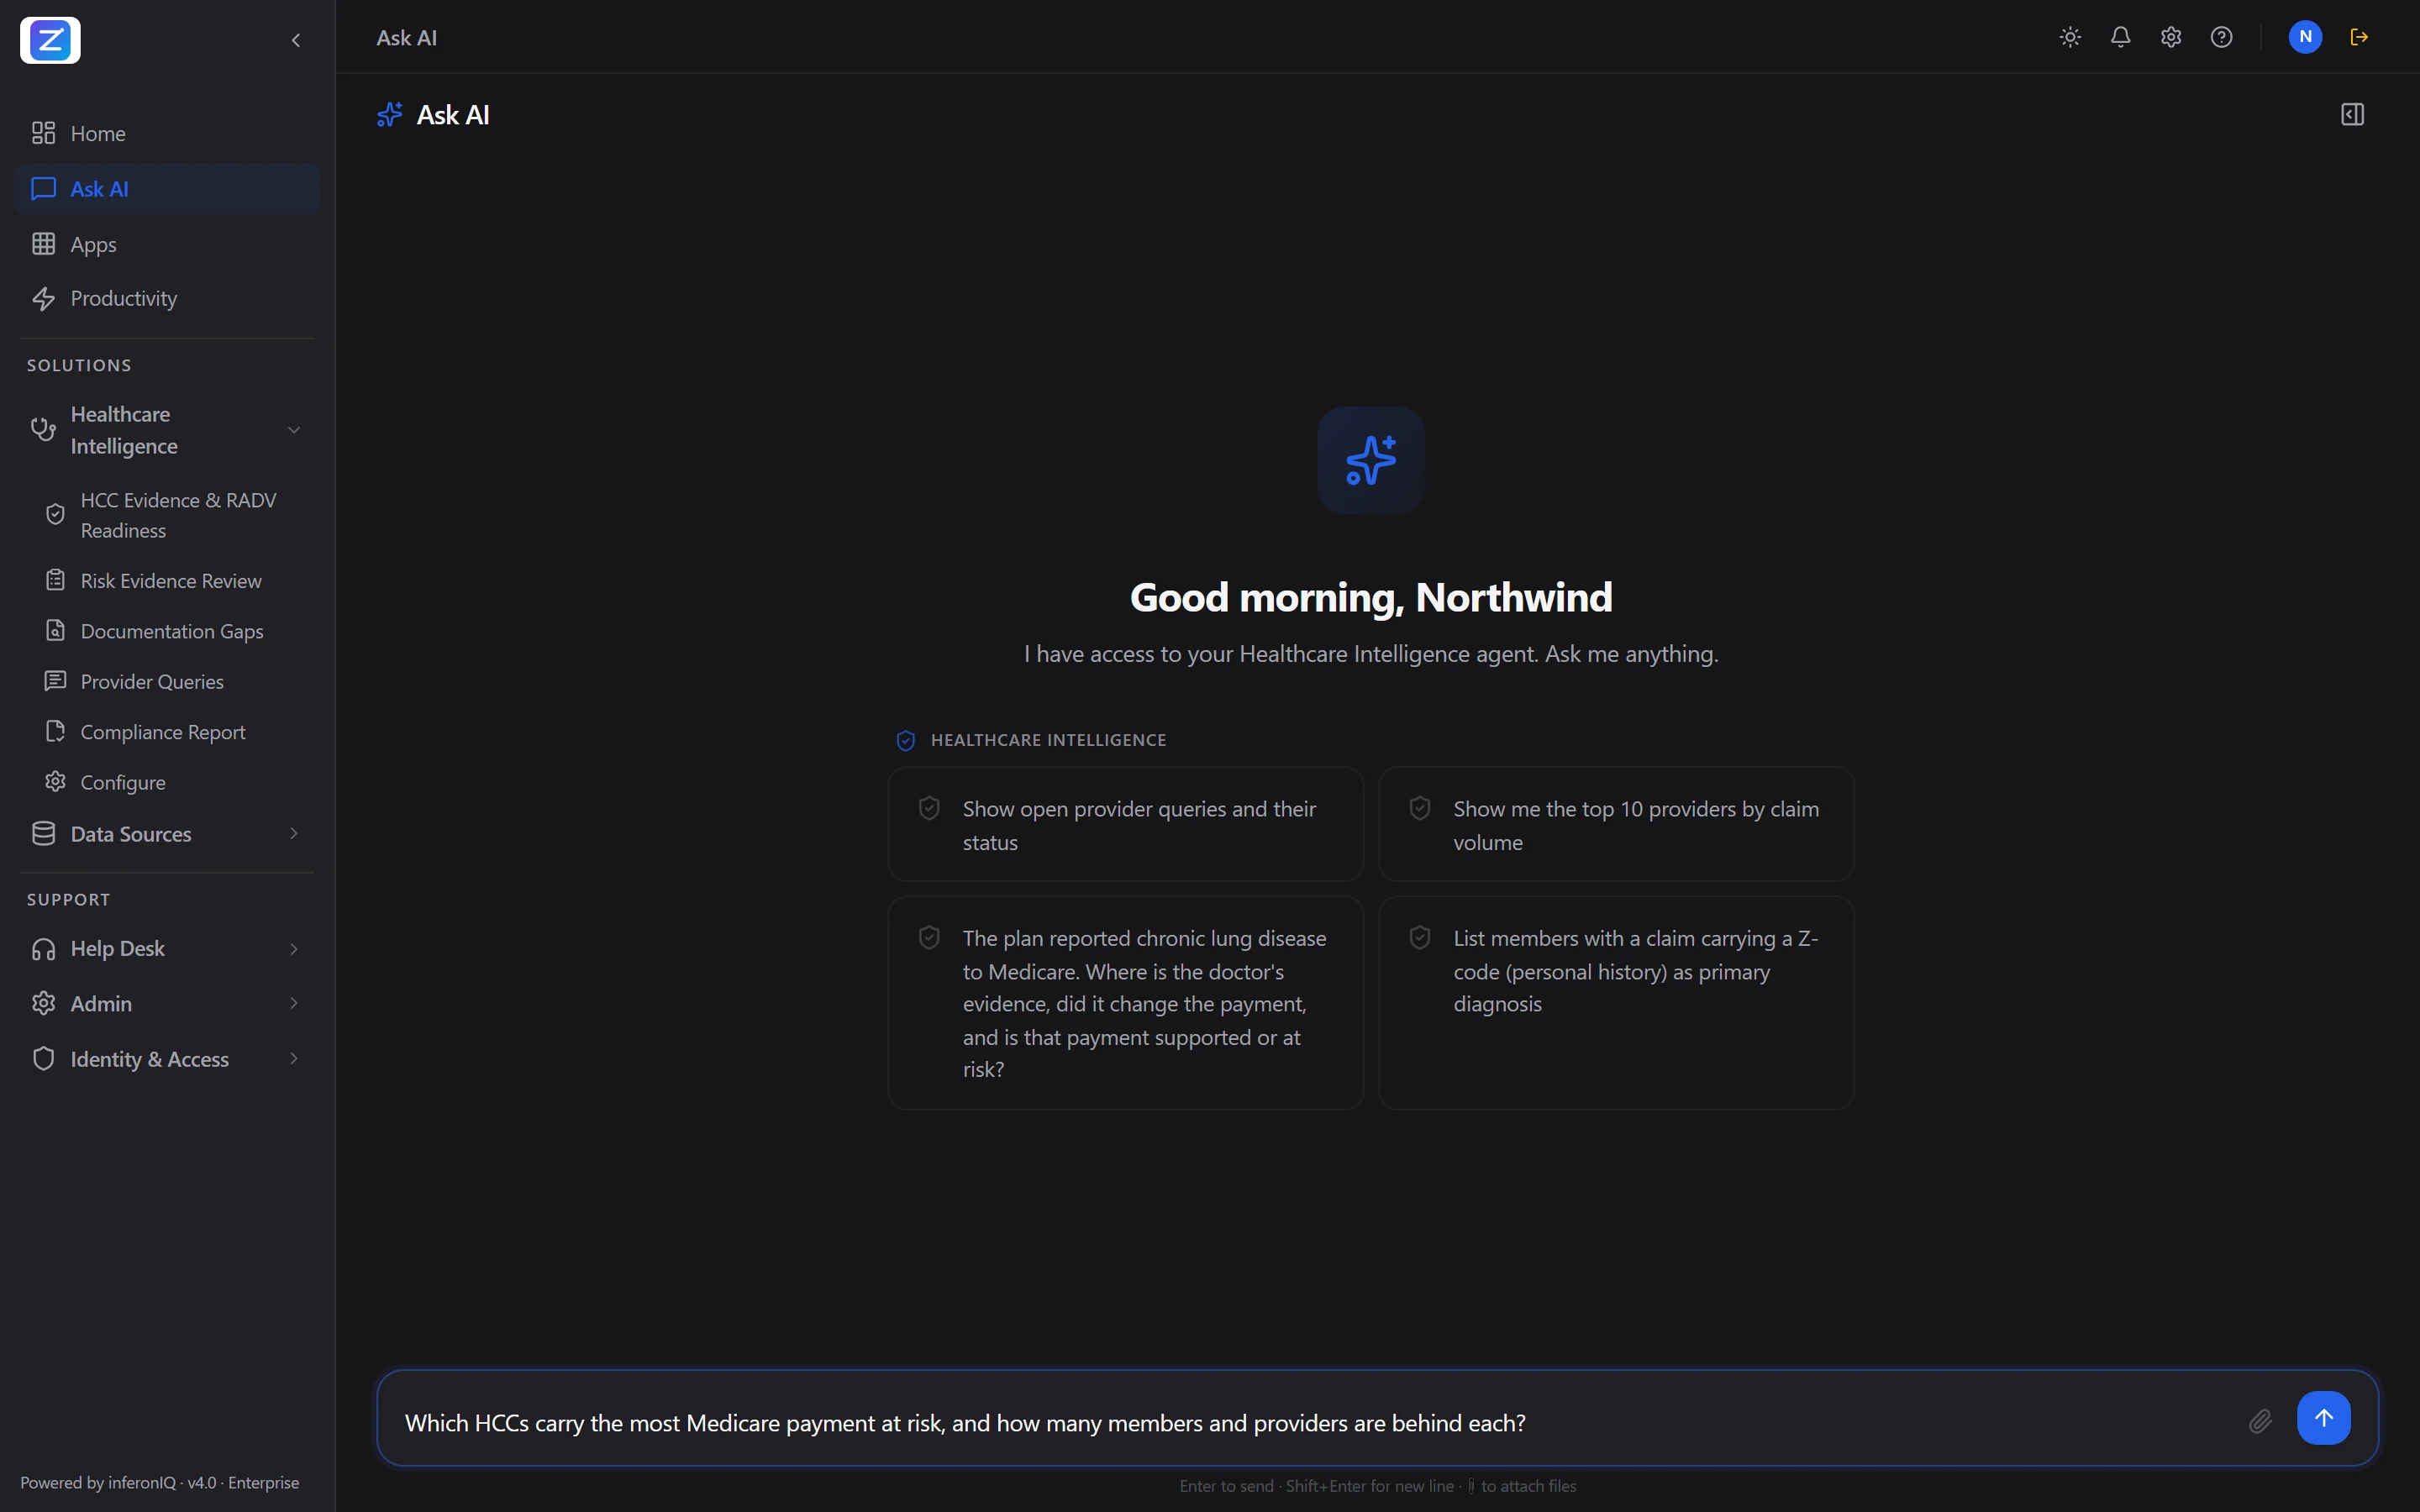
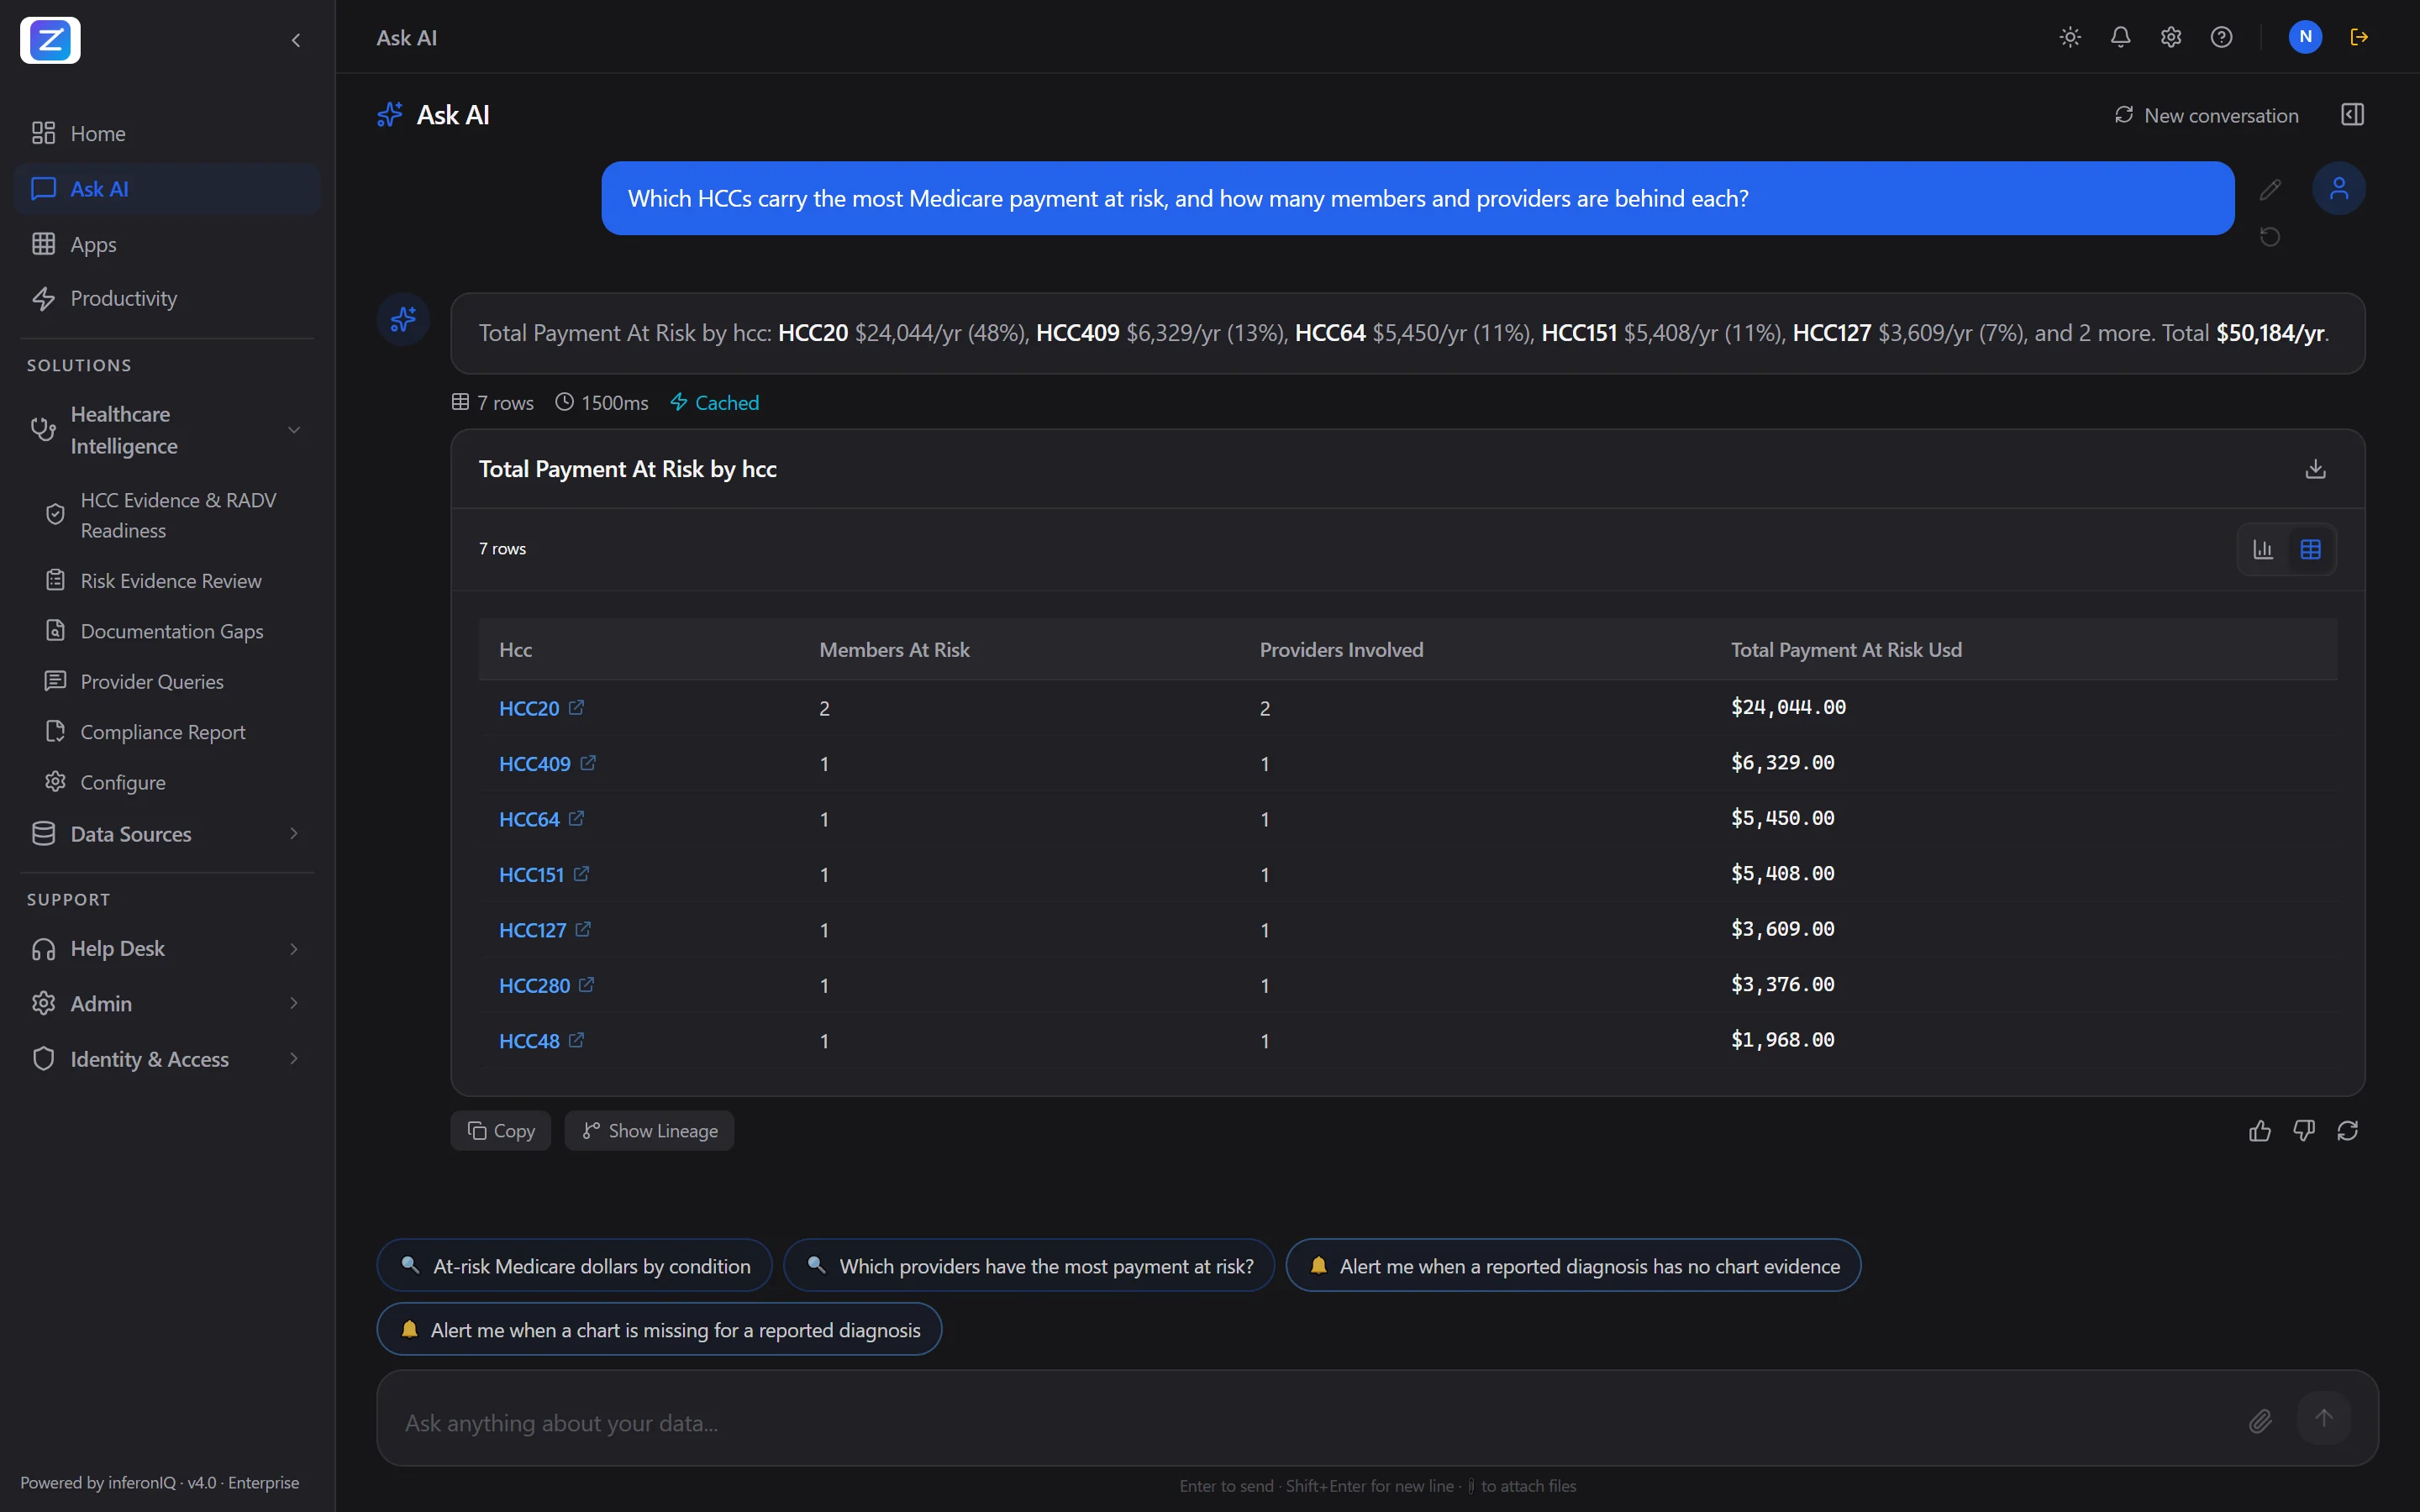
Captured from the live product on synthetic members and charts. No real patient data (PHI) is shown.
How we handle PHI.
The model sees only what the task needs, and every call is logged by task, provider and model, never by content.
BAA before any PHI
We sign a BAA with you, and every vendor that can see PHI signs one with us, before real patient data is loaded.
No retention, no training
Only AI providers you approve, under zero data retention. Your data never trains a model.
Masked, minimum necessary
Names, dates of birth and IDs are masked as placeholders before the model reads a chart header or summarises an answer. Writing SQL, it never sees patient records.
Rules decide, not the model
HCC mapping, hierarchies and dollar values come from CMS tables. A coder approves every finding.
Your cloud, your AI
Run InferonIQ in your own cloud (BYOC) with your own AI account. PHI never reaches InferonIQ; we receive only license checks.
Demos run on synthetic patients. See the FAQ for detail.
A diagnosis on the claim is not the same as a diagnosis the chart supports.
InferonIQ validates HCC-supporting documentation using MEAT-based evidence, ICD-10 to HCC mappings, source provenance and encounter context. Unsupported, conflicting, historical or incomplete diagnoses are flagged for human review — with the quoted text and page behind every call.
MEAT — Monitor, Evaluate, Assess, Treat — is the industry framework for judging whether documentation supports a diagnosis. It is not a CMS rule that every element must appear; CMS requires that submitted diagnoses be substantiated by the medical record. InferonIQ uses it to decide what a coder should look at, and a person makes the decision.
- M
Monitor
Home glucose log reviewed, fasting 140–180
Progress note · Assessment & plan · p.2
- E
Evaluate
A1C 8.1% · eGFR 52 mL/min
Lab panel · 2026-02-20 · p.4
- A
Assess
“DM2 with CKD 3a, not at goal”
Progress note · Assessment & plan · p.2
- T
Treat
Continue metformin 1000 mg BID; repeat A1C in 3 months
Medication list · p.3
“Diabetes mellitus” — problem list only, not discussed at the visit
Problem list · p.1
How you know the findings and the dollars are right.
RADV tests the whole program, not one code. InferonIQ checks the record, checks its own RAF arithmetic against CMS, puts a second reviewer on the decisions that matter and tracks every dollar from identified to realized.
Review quality
Every decision can stand a second look
- Checks the record itself
- Unsigned notes, RN, LPN or MA-only signatures and non-acceptable record types are held for review, citing CMS guidance.
- Second-level QA
- A different reviewer samples decisions, always including the high-value ones. A failed QA goes back to the queue.
- Every finding explains itself
- How to review it, the RAF calculation step by step, and a history of what changed it and why.
- Rules changes, previewed
- A locked benchmark shows exactly which cases change before a new rules version goes live.
Value ledger
Every dollar, from identified to realized
- Identified$5.1M
- Validated$3.8M
- Actioned$3.4M
- Resolved$3.3M
- Realized$3.2M
Each member, HCC and payment year is counted once. Illustrative figures on synthetic data.
RAF arithmetic equals CMS’s own V28 scorer on 954 test members across all seven segments.
Dollar values are estimates at your plan’s base rate. No accuracy figure is claimed on your charts until your own coders have measured it.
Outside coders see only the findings assigned to them, and only while a BAA is in force. Approved findings go out once, as FHIR R4 or CSV.
Choose which AI vendors may process your data. Nothing goes to any other vendor, even during an outage.
Where the exposure sits today.
Extrapolated
Unsupported HCCs before RADV
RADV findings are now extrapolated across the contract. A diagnosis without current-year MEAT evidence in the chart is no longer a single-claim problem — it is a plan-level exposure.
40+ hrs/week
Claims adjudication backlogs
Claims need 4-way validation — authorization, fee schedule, eligibility and clinical edits. Manual review misses unbundling, global-period violations and duplicate lines.
$1M–$5M/yr
GPO pricing non-compliance
Medical suppliers invoice at list instead of GPO-contracted rates across thousands of SKUs and hundreds of vendors.
Built for the teams who have to defend the number.
HCC Validation
Reconcile every reported diagnosis against encounters and the chart, map ICD-10 to CMS-HCC V28 for the payment year, apply CMS hierarchies and put a RAF and annual dollar value on every finding.
- ICD-10 → CMS-HCC V28 by payment year, hierarchies applied
- RAF and annual $ impact per finding, from official CMS tables
- Supported, unsupported, historical or conflicting
MEAT Evidence
Look for proof the provider monitored, evaluated, assessed or treated the condition — not just that it was listed. A problem-list or history-only mention is not accepted as support.
- Assessment & plan, labs, medications and imaging cited
- Quoted text with document and page
- Current-year date-of-service checks
Suspect Conditions
Surface diagnoses the chart documents — or pharmacy fills and lab results imply — that no claim carries, value each one in RAF and dollars, and send it to a coder, a chart chase or a provider query. Nothing is auto-coded.
- Documented but not submitted, or at the wrong specificity
- Pharmacy and lab signals with no claim (apixaban, eGFR, A1c)
- Opportunity valued net of V28 hierarchies
Documentation Gaps
Turn unsupported and chart-less diagnoses — and conditions only pharmacy or lab data shows — into a prioritized chart-chase worklist, send non-leading provider queries where the note falls short, and track every request until the returned chart has been reviewed.
- One request per chart, ranked by HCC and RADV risk, dollar value shown
- CSV export and status re-import for retrieval vendors
- Returned charts matched and re-reviewed automatically
RADV Readiness
Trace every finding back to member, encounter, document, page and evidence before an auditor asks for it.
- Member → encounter → page provenance
- Readiness score across open findings
- Evidence export with reviewer decisions
Evidence Assurance
Prove the program itself is right: the record is checked, the RAF arithmetic is checked against CMS, a second reviewer samples decisions and every dollar is tracked from identified to realized.
- Signature, credential and record-type checks, citing CMS guidance
- RAF arithmetic equals the CMS V28 scorer on 954 test members
- Second-level QA and a value ledger, each member / HCC / year counted once
Reviewer Guidance & History
Every finding explains itself: what Agree and Disagree mean, how to review it, the RAF calculation step by step, and a history of what changed it and why.
- “How to review this finding”, written for the coder
- Step-by-step RAF and estimated dollar calculation
- Change history with the cause: rules, CMS / ICD release, base rate, segment or a new chart
Healthcare Ask AI
Ask questions across claims, encounters, labs, medications and clinical documents in plain English.
- Claims + chart in one question
- Governed, PHI-aware answers
- Every number traced to its source
- Record needed
- Requested
- Received
- Analyzed
- Closed
M-20418 · Office visit · DOS 2026-03-14
HCC 37 · HCC 329 · No chart on file
HighRecord neededM-11873 · Cardiology consult · DOS 2026-01-22
HCC 226 · No current evidence
HighRequestedM-30952 · Office visit · DOS 2026-02-05
HCC 409 · Amputation status undocumented
MediumReceivedM-09617 · Office visit · DOS 2025-12-09
HCC 155 · Insufficient evidence
LowAnalyzed
When the evidence is not in the chart, go and get it.
Unsupported findings and claims with no chart on file become one record request per encounter, ranked by HCC value, RADV sensitivity and date of service.
- Filter and export a retrieval list for your vendor or provider outreach team
- Re-import statuses from the vendor file; nothing is re-keyed
- Returned charts are matched to the open request and re-reviewed automatically
- Each request is timestamped at every stage, from record needed to closed
Evidence in. Reviewed action out.
Every diagnosis is reconciled across claims, encounters and the chart, evaluated against HCC rules and MEAT criteria, and classified into a finding a coder can act on — with the evidence ready for audit when it is approved.
- 1ConnectClaims · Encounters · Labs · Medications · Clinical PDFs
- 2UnderstandDocument AI · Clinical concepts · ICD-10 · Member timeline
- 3ReconcileClaims ↔ Encounter ↔ Clinical evidence
- 4EvaluateHCC rules · MEAT · Current-year evidence · Conflicts
- 5FindingsClassified, evidence-linked, ranked by impactSupportedUnsupportedMissing candidateHistoricalConflictNeeds review
- 6ActCoder review → Record request → Provider query → Audit evidence
Ask across claims and the chart in the same sentence.
The same NL2SQL and Document AI engine behind Enterprise Intelligence, tuned for clinical vocabulary. Structured tables and unstructured notes are answered together, and every number links back to the rows and pages it came from.
Risk Adjustment
Which reported HCCs lack current-year clinical evidence?
RADV
Show every document supporting HCC 85 for this member.
Coding
Which members have diabetes complications documented but not coded?
Suspects
Which members have pharmacy or lab evidence of a condition nobody documented this year?
Designed for audit from the first query.
Every finding has a source
Member, encounter, document, page and quoted text are attached to each result. Nothing is asserted without evidence.
People make the call
AI proposes; coders and reviewers approve, correct or reject. Every decision is attributed and timestamped.
Full audit trail
Every chart read by AI (model, time and the exact output), Ask AI questions and answers, reviewer and QA decisions and exports are logged for compliance and RADV defence.
Read-only connections
Connectors read from EHR, claims and document stores. Corrections flow through your existing systems.
The same deployment covers the business side.
Provider groups and hospital networks use Enterprise Intelligence alongside clinical review — for payment integrity, supplier pricing and contract terms.
Claims & payment integrity
Authorization, fee schedule, eligibility and billed amount reconciled per claim line. Unbundling and duplicate lines flagged before payment.
Learn moreSupplier & GPO pricing
Medical-supply invoices checked against GPO tier and contract rates across every facility and SKU.
Learn moreImplant & device billing
Device and implant invoices validated against surgical logs, quantities and authorized substitutions.
Learn morePayer & supplier contracts
Terms, escalators, renewal dates and obligations extracted from agreements and monitored against actual spend.
Learn moreSpinal implant claim: authorization approved, GPO fee schedule $3,950, eligibility active, billed $4,800 — an $8,500 overcharge across 10 units, caught before payment.
Claims and supply checks that run on every line
- 4-way claims match: authorization ↔ fee schedule ↔ eligibility ↔ claim
- WAC pricing variance — invoices above wholesale acquisition cost
- Cold-chain, hazmat and controlled-substance surcharge detection
- GPO tier-rate compliance on every medical-supply invoice
- Implant and device billing validated against surgical logs
- Duplicate claim and line-item detection
- Supply PO ↔ receipt ↔ invoice 3-way match across facilities
- Tolerances configurable by category, vendor and facility
Ask operations
- Show claims denied for missing authorization in the last 90 days
- Which suppliers are invoicing above GPO contract rates?
- What implant invoices have quantity mismatches vs surgical logs?
- Show providers with the highest unbundling rate this quarter

Clinical review and payment integrity, from one deployment.
Health plans, provider groups and hospital networks.
Not a second product. The same platform.
Healthcare Intelligence runs on the NL2SQL, Document AI, Agent Studio, workflow and governance layers that power Enterprise Intelligence — so revenue-cycle, supply-chain and contract teams can work from the same deployment.
Healthcare Intelligence — frequently asked questions
MEAT, V28, RAF dollars, chart chase, provider queries, evidence assurance, RADV and PHI
How do we know the findings and dollar values are right?
What is MEAT in risk adjustment?
Does InferonIQ support CMS-HCC V28?
How is the RAF dollar value of a finding calculated?
What is a chart chase, and how does InferonIQ help?
Can pharmacy and lab data find suspect conditions?
How do provider queries work? Is this CDI?
Does InferonIQ code charts automatically?
How does InferonIQ help with RADV audits?
Which data sources does it connect to?
Will you sign a BAA?
Do you send PHI to AI models?
Where does our PHI live?
Does InferonIQ support ACA (HHS-HCC) risk adjustment?
Have more questions? Contact us
See it on a real evidence review.
We will walk your team through a scoped HCC evidence review — on sample or de-identified data, in our cloud or yours — and every finding behind it.